


Cruise ships carry their own hospitals, complete with beds, oxygen, and staff trained for everything from a twisted ankle to a cardiac event. Yet doctors who work these floating clinics keep seeing the same pattern: passengers wait far too long before walking through the medical center door. Vacation mode has a way of talking people out of asking for help, right up until a small problem turns into a much bigger one.
Onboard physicians rarely talk publicly about specific patients, but industry data and firsthand accounts from ship doctors point to a handful of complaints that consistently get ignored until they can’t be. Here are six of them, and why waiting almost never pays off.
1. Seasickness that has already caused dehydration
Motion sickness is not a minor nuisance on cruise ships. It is the reason for most visits, especially first-time cruisers still getting their sea legs[1], and it shows up early in a voyage before most passengers have found their footing. The instinct is to tough it out with crackers and ginger ale, sometimes for days, rather than admit defeat and head to Deck 2.
The trouble is that repeated vomiting is not just uncomfortable, it drains fluids fast. The problem is that repeated vomiting from motion sickness causes real dehydration, not just discomfort, and doctors say passengers often wait until they can’t keep water down for a full 24 hours before asking for help, at which point they need IV fluids instead of a simple patch or pill.[2] Medical staff say the fix is far simpler earlier on, when oral medication or a quick injection can still turn things around before the body starts running on empty.
2. A blister that starts looking angry, not just sore
Nobody thinks a blister from new sandals deserves a doctor’s visit, so most people cover it with a bandage and keep exploring. On a cruise, though, the conditions are almost designed to make a small wound worse. Cruise medical staff see this constantly during Caribbean and Mediterranean itineraries, where passengers rack up 15,000+ steps a day in flip-flops.[2]
Heat, humidity, and pool chlorine create an environment where bacteria thrive, and a blister does not stay a blister for long. A simple foot blister can turn into cellulitis within 48 hours in warm, humid conditions.[2] Once that happens, treatment stops being a bandage and becomes a course of antibiotics, some of which can interact with the very seasickness medication a passenger might already be taking.
3. Sunburn severe enough to affect the whole body
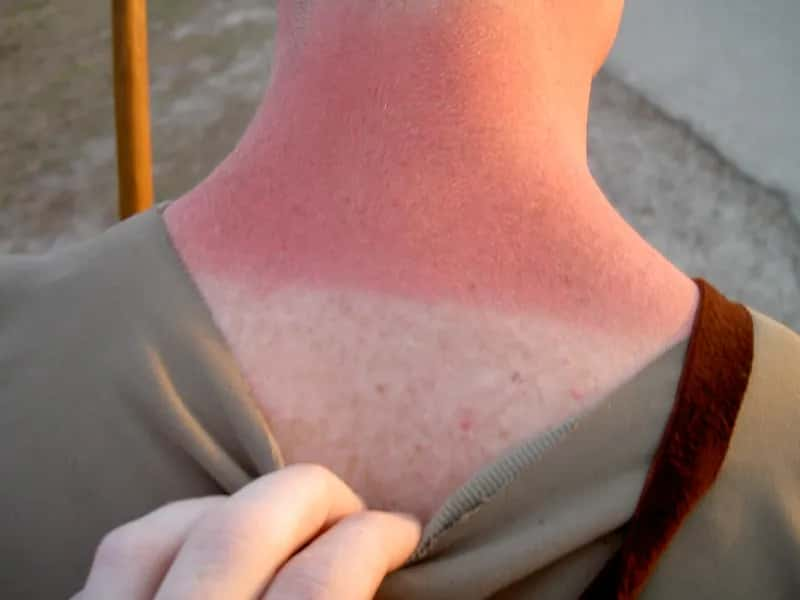
A bad sunburn on day one often gets treated as an annoying cosmetic problem rather than a medical one. Passengers slap on aloe and move on to the pool bar, not realizing the skin damage can interfere with something far more basic than appearance. Severe sunburn can raise skin temperature enough to interfere with normal sweating and cooling.[2]
The real danger shows up the next day, often at a hot port stop where the ship’s cooling systems and shade are no longer around. Severe sunburn disrupts the body’s ability to regulate temperature, setting the stage for heat exhaustion the very next day at a hot, humid port, while nausea and dizziness get blamed on the cruise food instead, a combination ship doctors call one of the most predictable, and most avoidable, reasons people end up needing IV fluids.[2] A short visit to the clinic for burn care ahead of a big shore excursion can prevent that entire chain reaction.
4. Leg swelling that only affects one side

Long flights to the port, followed by sea days spent sitting by the pool or in a theater seat, add up to hours of near-total inactivity. Most passengers chalk up puffy legs to salty ship food or general travel bloat and think nothing more of it. Long flights followed by days of sitting at the pool or in a theater seat create the exact conditions for leg swelling, and most passengers assume it’s just fluid retention from salty ship food.[2]
When the swelling is uneven, though, doctors treat it very differently. Doctors say this is one of the more concerning complaints to see delayed, because sudden one-sided swelling can signal a blood clot rather than simple bloating, and it is treated as a possible clot risk, not a cosmetic issue, by onboard medical teams.[2] The guidance from ship staff is straightforward: move around during sea days, and do not sit on swelling that feels off for more than a day before getting it looked at.
5. A toothache that seems too small to bother the doctor with
Dental pain is one of the most postponed complaints on any ship, mostly because passengers assume there is nothing a physician without a dentist’s chair can actually do. Dental pain is one of the most commonly delayed complaints on any ship, mostly because passengers assume there’s nothing a cruise doctor can do about it.[2] So people grit their teeth, quite literally, and plan to deal with it once they are back home.
That delay can turn a manageable ache into a much rougher few days at sea, especially on longer itineraries where home is still a week away. Onboard medical teams can usually offer pain control, anti-inflammatory treatment, or antibiotics if there are early signs of infection, buying time until proper dental care is available. Waiting it out with over-the-counter painkillers alone tends to just prolong the discomfort rather than resolve it.
6. A cough or chest congestion that lingers past a day or two

Respiratory symptoms are easy to dismiss on a cruise, where recycled air, close quarters, and crowded buffet lines make a stuffy nose feel almost inevitable. Passengers often wait it out with lozenges and an extra nap, assuming it will pass on its own. The data suggests otherwise: respiratory illnesses are the most common medical complaint on cruise ships[3], which means ship doctors are well equipped to treat them, but only if passengers actually come in.
Health authorities are direct about the timing here. Cruise ship passengers should report respiratory illness to the medical center promptly and follow isolation recommendations as instructed[3], both to get appropriate treatment and to limit spread in an environment where thousands of people share ventilation systems and dining rooms. A cough that seems minor on day one can also mask something like early pneumonia in older travelers, which is part of why medical teams prefer an early look over a guessing game later in the cruise.
Across all six of these situations, the common thread is the same. None of these symptoms are the dramatic, sirens-blaring emergencies people picture when they think about a ship’s medical center. They are the quiet, easy-to-explain-away kind, which is exactly why they get ignored until a same-day visit becomes an IV drip, a course of antibiotics, or a longer recovery than anyone planned for. Ship doctors are not judging anyone for the wait. They are simply pointing out that the earlier version of most of these problems is almost always the easier one to treat.



